

From
StayCurrentMD
Compiled Sandler Rapid Fire Sessions: Update Course 2015
With Dr. Tony Sandler · hosted by Dr. Todd Ponsky
Educational content from recorded physician discussions — not medical advice. Talk to your (or your child's) care team about your situation.
Video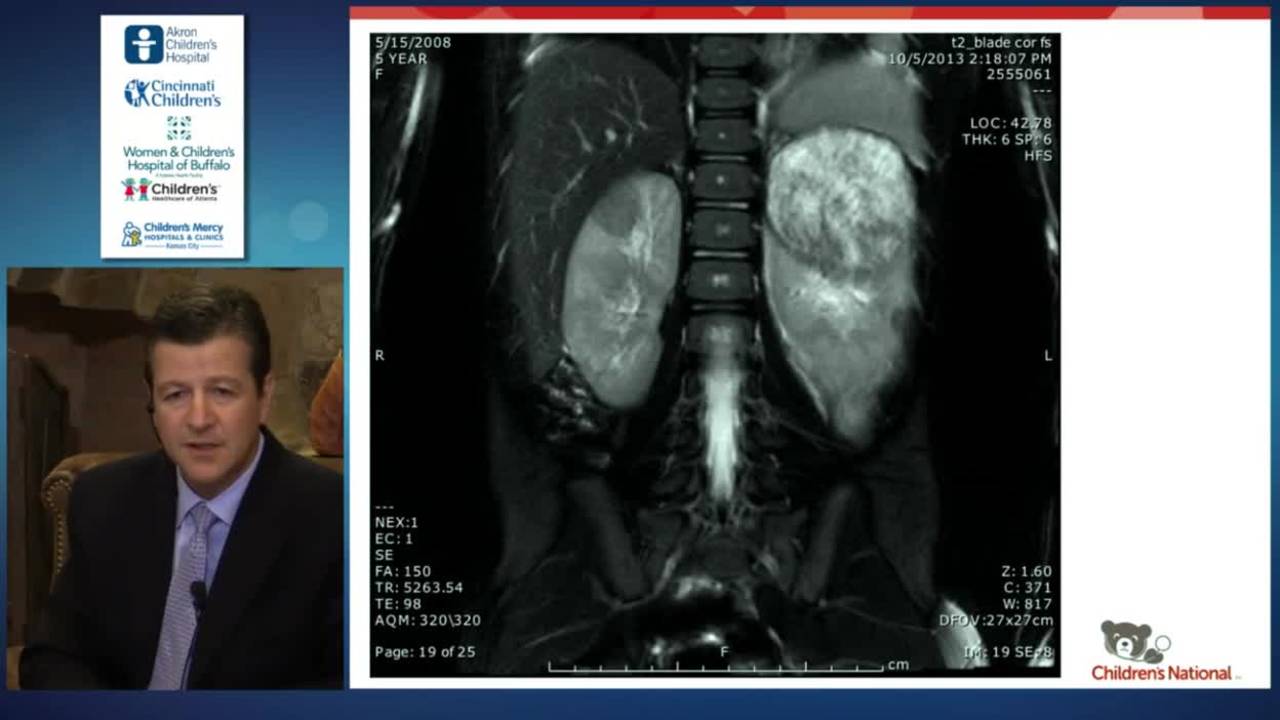
Wilms Tumor Rapid Fire: Update Course 2015
8 min · Published Nov 2015
Video
Impact of Pulmonary Tumor Burden in Favorable Histology Wilms Tumor Outcomes: A Report From the Children's Oncology Group Study AREN053
1 min · Published Mar 2026
Video
Updated Favorable histology Wilms tumor risk stratification: Rationale for future Children’s Oncology Group clinical trials
53 s · Published Apr 2026
Video
Update Course 2021: DEI – CONCORDANCE AND POST OP COMPLICATION STUDIES
Published May 2022
Video
Update Course Rewind: Lipiodol for Lung Metastases 2024
Published Jan 2025
Podcast
Wilms Tumor: Audio Chapter
64 min · Published Jun 2017
Video
Clinical & Research Update: Renal Tumors with Drs. Ethan Smith, Lindsay Haacker, Michael Daugherty, and Meera Kotagal
71 min · Published Sep 2026
Video
Clinical & Research Update: Neuroblastoma with Drs. Katherine Somers, Cara Morin, Juan Gurria, and Meera Kotagal
67 min · Published Sep 2026
Video
Clinical & Research Update: Sarcoma w/ Drs. Roshni Dasgupta, Joseph Pressey, Arthur Meyer, Luke Pater
66 min · Published Sep 2026
Video
Update Course Rewind 2025: Nerve Monitoring in Pediatric Thyroid Surgery
6 min · Published Jul 2026
Video
Journal of Pediatric Surgery Article Review: June 2023, AAP Issue
Todd Ponsky · 13 min · Published Jul 2026
Video
Pediatric Surgical Oncology Research Collaborative (PSORC): Studying Rare Pediatric Tumors
56 s · Published May 2026
Video
Intestinal Atresia Types Explained: Grossfeld Classification for Pediatric Surgery
1 min · Published Sep 2026
Video
Derivation and validation of the Pediatric Community-Acquired Pneumonia Severity (PedCAPS) score: A prospective cohort study
50 s · Published Sep 2026
Video
FETO for Late-Diagnosed Severe Congenital Diaphragmatic Hernia (CDH) at Cincinnati Children's with Dr. Beth Rymeski
4 min · Published Sep 2026
Video
Severe Congenital Diaphragmatic Hernia (CDH) Case: FETO Management & Unexpected Findings with Dr. Beth Rymeski
3 min · Published Sep 2026
Video
Fetoscopic Endoluminal Tracheal Occlusion (FETO) Procedure: Step-by-Step Guide with Dr. Beth Rymeski
4 min · Published Sep 2026
Video
Choledochal Cyst Types Explained: Pediatric Surgery Fundamentals
1 min · Published Sep 2026
What the experts said
Current standard for bilateral Wilms tumor is to start chemotherapy without biopsy, typically 2 cycles, and continue until tumor shrinkage plateaus (defined as less than 50% size reduction)
Wilms tumors are heterogeneous and biopsy may miss foci of anaplasia
When Wilms tumors stop shrinking with chemotherapy, it is usually due to mesenchymal differentiation rather than anaplastic transformation
Bilateral nephron-sparing surgery is feasible even in large bilateral Wilms tumors by placing kidneys on ice, clamping vessels, and performing sharp dissection
Recurrence of anaplastic Wilms tumor portends a very bad outcome and salvage is difficult despite chemotherapy
Most pathologists believe anaplasia in Wilms tumor is present primarily rather than induced by chemotherapy
Multifocal Wilms tumors raise concern about underlying embryologic abnormalities of the kidney and risk of developing additional tumors
97% of bilateral kidney tumors in children are Wilms tumor, with only a small percentage being other diagnoses
For gastroschisis with inflamed bowel, bedside reduction without intubation is feasible using rectal Tylenol and minimal fentanyl
In many centers, high-risk obstetric teams deliver gastroschisis cases early by C-section, resulting in less thick and matted bowel at birth
For gastroschisis reduction at bedside, babies are intubated and paralyzed, a stitch is placed in the fascia with cord left as a biological patch, and Opsite dressing is applied; patients are kept paralyzed for 1-2 days
Umbilical hernias after gastroschisis closure will close spontaneously if no fascia was cut; if fascia is cut, a permanent defect results
Spring-loaded Bianchi silos may enlarge the fascial defect because the outward forces from the compressed ring push laterally
Tegaderm closure of gastroschisis without fascial closure allows cicatrization over 3 days to 8 weeks, with feeding started when bowel function returns rather than waiting for complete closure
When gastroschisis defect dilates during silo reduction attempts, Tegaderm closure alone can still achieve successful cicatrization without fascial closure
In gastroschisis with intestinal atresia and pristine bowel, creating an ostomy through the umbilical fascial ring is technically favorable because the bowel size matches the ring and provides good tissue for suturing
Primary anastomosis in gastroschisis with atresia is risky because the proximal bowel is massively dilated and distal bowel is decompressed, creating a tenuous anastomosis in bowel that has been outside the abdomen
In vanishing gastroschisis with markedly inflamed bowel, it is impossible to determine bowel viability or the extent of remaining intra-abdominal bowel from external examination
Re-exploration at 2 weeks after gastroschisis closure (rather than the traditional 4-6 weeks) can reveal that inflamed gastroschisis bowel has transformed into functional intestine suitable for anastomosis
Plication of dilated bowel in ileal atresia usually unravels with time, allowing the bowel to be used later for lengthening procedures
Bianchi procedure is preferred over STEP for bowel lengthening because a patient can undergo Bianchi followed by STEP if needed, but once STEP is performed, lengthening options are limited
In neonatal ileal atresia with dilated proximal bowel, plication is preferred over tapering to preserve bowel length for potential future lengthening procedures
The STEP registry discourages performing STEP procedures in the perinatal period due to difficult outcomes at best
STEP procedures in patients with gastroschisis are not particularly beneficial due to underlying motility disorders